The European Society of Intensive Care Medicine (ESICM) has introduced a new consensus statement advocating for a transition from conventional patient-focused care to a more expansive human-centered approach within intensive care units (ICUs). This framework, published in Intensive Care Medicine in October 2026, places equal emphasis on preserving dignity, supporting open communication, and addressing emotional well-being alongside clinical proficiency.
Expanding Care Beyond Medical Outcomes
Though technological advancements in monitoring and organ support have driven survival rates upward, critically ill patients and their families frequently endure psychological strain, communication obstacles, and ethical dilemmas. The consensus makes clear that effective care extends beyond medical results—it must actively confront fear, respect patient autonomy, and promote shared decision-making. Meanwhile, healthcare workers face rising burnout and compassion fatigue, showing the need for systemic support structures.
The recommendations emerged from a methodical review involving 46 specialists from 20 countries, who examined 20 studies across domains including person-centered care, communication strategies, psychological resilience, equity, ICU environments, and technological integration. After two rounds of stakeholder consultation, 43 consensus statements were established.
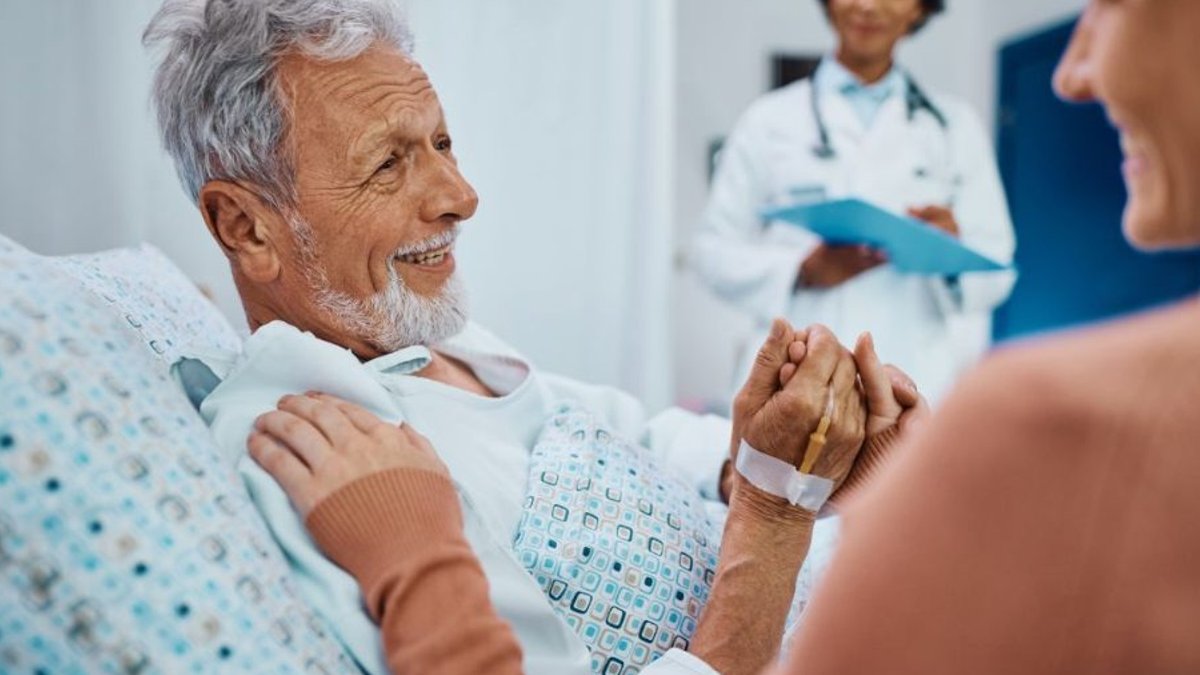
A fundamental change involves treating patients and families as collaborative partners rather than passive recipients. Since critically ill patients may be sedated or unable to articulate their wishes, the consensus insists on early documentation of their values and preferences. It also advocates for family participation in treatment decisions and flexible visitation policies to counteract isolation.
Prioritizing Communication and Psychological Care
Clear, structured communication between clinicians and families is especially vital during prolonged illnesses or end-of-life discussions. The guidelines propose empathy-based training for staff to better manage emotional distress and cultural differences. They also recognize the lasting psychological toll on survivors, such as post-intensive care syndrome, and families, who may develop anxiety or PTSD.
Read Also: Doctors test safer fluid limits in septic shock care
Staff well-being receives equal attention. The document highlights how excessive workloads and moral distress can diminish compassion, calling for organizational support and workload management. Without addressing these challenges, even well-designed care models risk collapse.
The consensus also stresses equity and inclusivity. Standardized ICU protocols may neglect patients with diverse health literacy, cultural backgrounds, or language barriers. To ensure respectful and accessible care, it recommends culturally adapted communication and information delivery.
Design and Technology: Supporting Human Connection
The ICU’s physical environment, excessive noise, artificial lighting, and unfamiliar surroundings, often exacerbates patient distress and delirium. The statement supports interventions like sleep optimization and comfort-focused redesign to create a more supportive atmosphere. While digital tools can improve collaboration, their use must never displace human interaction or compromise dignity.
Technology should serve as an adjunct to, not a replacement for, meaningful relationships. Virtual platforms, for instance, should complement rather than replace in-person communication between patients, families, and clinicians.
Implementation will differ across institutions due to variations in resources, staffing, and cultural norms. The consensus acknowledges that some recommendations lack strong evidence, necessitating local adaptation instead of uniform adoption. Nonetheless, its central argument remains unchanged: survival rates alone cannot measure high-quality care.